
Abstract
Aim One of the earliest symptoms of acute carbon monoxide (CO) poisoning is headache. In this study, we aimed to identify cases of CO poisoning by examining SpCO levels as a new vital parameter in patients presenting with headaches, to detect cases that might otherwise be overlooked, and to facilitate early diagnosis and treatment.Methods Our prospective cross-sectional study was conducted during the winter of 2019-2020 (December 2019 through February 2020). A total of 104 patients who met the inclusion criteria and did not meet the exclusion criteria were included in the study. Demographic data, admission times, symptom onset times and severity, smoking status, SpCO measurements, COHb levels, oxygen saturation levels, suspected sources of exposure, and patient outcomes were recorded on the study form. Statistical data analysis was performed using SPSS (Statistical Package for the Social Sciences) version 22.0.Results Elevated SpCO levels were detected noninvasively in 7 patients (6.7%), whereas elevated COHb levels were detected by blood gas analysis in 8 patients (7.6%).Conclusion Measuring SpCO levels as a new vital parameter in patients presenting with isolated headaches can help detect CO poisoning cases that might otherwise be overlooked and enable early diagnosis and treatment.
Keywords
Introduction
Carbon monoxide (CO) is endogenously synthesized in the human body through the action of the heme oxygenase enzyme and is involved in various biological processes, including neurotransmission and vasodilation. However, exposure to elevated CO levels from exogenous sources can cause toxic effects.1 One of the earliest symptoms of acute CO poisoning is headache.2 Headaches have also been reported with low-level CO exposure, which is particularly common during winter. The molecular mechanism underlying CO-induced headaches has not yet been fully elucidated. It is hypothesized that CO may contribute to pain signaling through interactions with cyclic guanosine monophosphate (cGMP) pathways and nitric oxide, both of which are important in the pathophysiology of primary headaches.3-5 Additionally, CO inhalation has been shown to increase cerebral blood flow by approximately 26%.6 Autopsy studies further support this, demonstrating the vasodilatory effects of CO on both cerebral and peripheral arteries.7
Headache is a significant public health issue that affects individuals across all socioeconomic and age groups, prompting nearly 47% of adults to seek care in emergency departments.8 In high-volume emergency settings, life-threatening causes of headaches, such as CO poisoning, may be overlooked due to patient overload and diagnostic challenges.9 Since the diagnosis of CO poisoning often relies on a high index of suspicion based on the patient’s history, it is frequently misdiagnosed or attributed to other primary headache disorders in emergency departments. Incorporating transcutaneous CO measurement into triage protocols could be helpful in such cases.
In this study, we aimed to evaluate the utility of transcutaneous CO measurement as a potential adjunctive vital parameter for the early detection of CO poisoning in patients presenting to the emergency department with headaches.
Materials and Methods
Study Design and SettingOur study was conducted prospectively in the winter months (December, January, and February). The study was conducted in an emergency department with a mean annual volume of 250,000 to 300,000 patient visits.ParticipantsOf 45,600 patients who presented to the emergency department with a green-zone triage classification, 104 patients with isolated headaches who met the inclusion criteria and had no exclusion criteria were enrolled. Patients aged 18 and over who presented to the green zone with isolated headache complaints, regardless of suspected CO poisoning, and agreed to participate in the study were included. Pregnant women and patients who left the hospital before study completion were excluded.Data Sources/MeasurementsPatients’ CO levels were transcutaneously and noninvasively measured using the Masimo Radical-7 Pulse CO-Oximeter (Masimo Corporation, Irvine, California, USA). Patients with a SpCO value above 3% underwent invasive blood gas analysis, regardless of smoking status. Levels up to 3% were considered non-toxic in non-smokers, whereas levels up to 10% were deemed non-toxic in smokers and tobacco users.10
Headache severity was assessed using the Numeric Rating Scale (NRS). The study form recorded demographic information, time of presentation, symptom onset time, tobacco product use status, transcutaneous CO measurement values, COHb levels, measurement times (noninvasive and/or invasive), oxygen saturation levels, suspected sources of exposure, and patient outcomes.BiasNo selection bias was introduced, and no preference was given to any specific patient group.Ethical ApprovalThis study was approved by the Ethics Committee of İzmir Katip Çelebi University (Date: 12.05.2020; Decision No:640).Statistical AnalysisStatistical analyses were performed using the Statistical Package for the Social Sciences (SPSS), version 26 (IBM Corp., SPSS Inc., Chicago, IL, USA). Categorical variables were presented as frequencies and percentages, while continuous variables were expressed as mean and standard deviation. The Kolmogorov-Smirnov and Shapiro-Wilk tests were used to assess the normality of data distribution. The Chi-square test was used to compare categorical variables. A P value ≤ .05 was considered statistically significant.Reporting GuidelinesThis study was reported in accordance with the STROBE guidelines.
Results
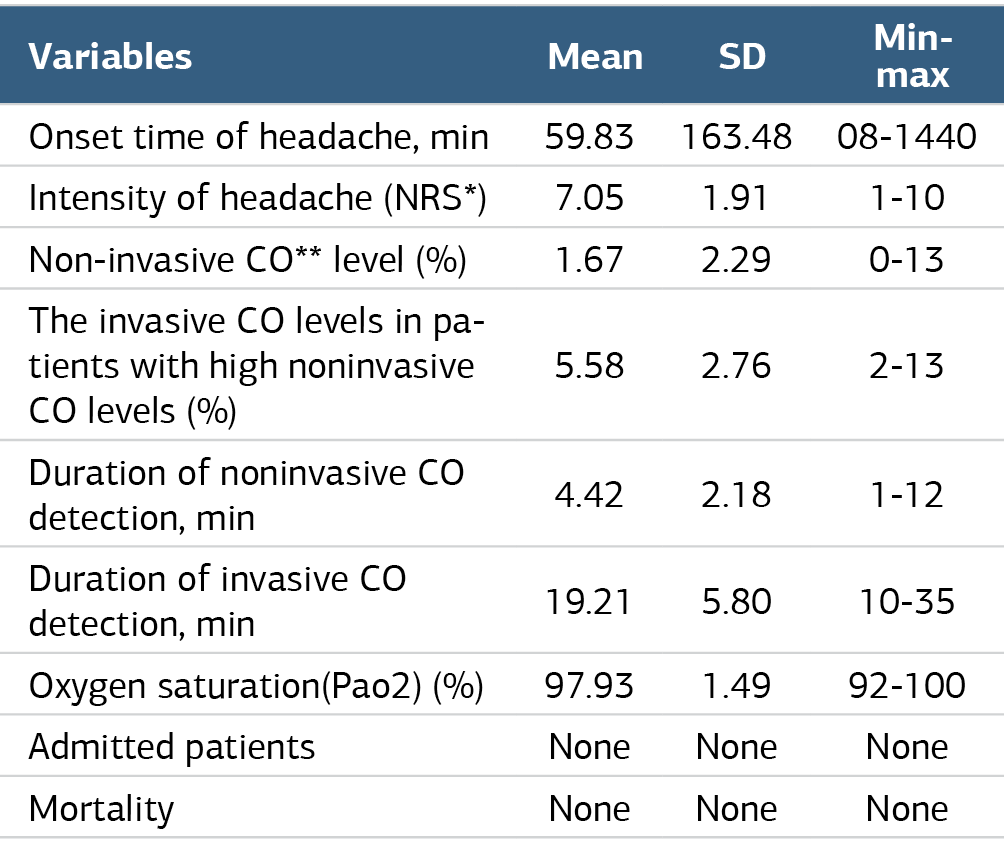
Of the 45,600 patients who presented to the green zone of the emergency department, 104 patients with isolated headaches who met the eligibility criteria were included. Among these 104 patients, 7 (6.7%) had elevated SpCO levels detected noninvasively, while 8 (7.6%) had elevated COHb levels confirmed through invasive measurement. Of the included cases, 68 (65.4%) were female, and 36 (34.6%) were male. The mean age of the participants was 37.6 ± 13.9 years (range: 18–74). Among the eight patients with elevated CO levels, 75% were female (n = 6), and 25% were male (n = 2). The mean age of these eight patients was 41 ± 16.31 years.
In our study, the mean COHb level, measured by venous blood gas analysis, in patients with elevated SpCO levels was 5.58 ± 2.76%. In two patients who did not use tobacco products, while the SpCO level was found to be low, one patient had an elevated COHb level on invasive measurement. Conversely, one patient had a high SpCO level despite a low invasive COHb level.
When noninvasive CO measurement times were analyzed, values ranged from 1 to 12 minutes, with a mean detection time of 4.42 ± 2.18 minutes. The time required for invasive CO measurement ranged from 10 to 35 minutes, with a mean duration of 19.21 ± 5.80 minutes. The mean oxygen saturation level of patients presenting with headaches was 97.93 ± 1.49% (range: 92–100%). No hospital admissions or mortality occurred in our study (Table 1).
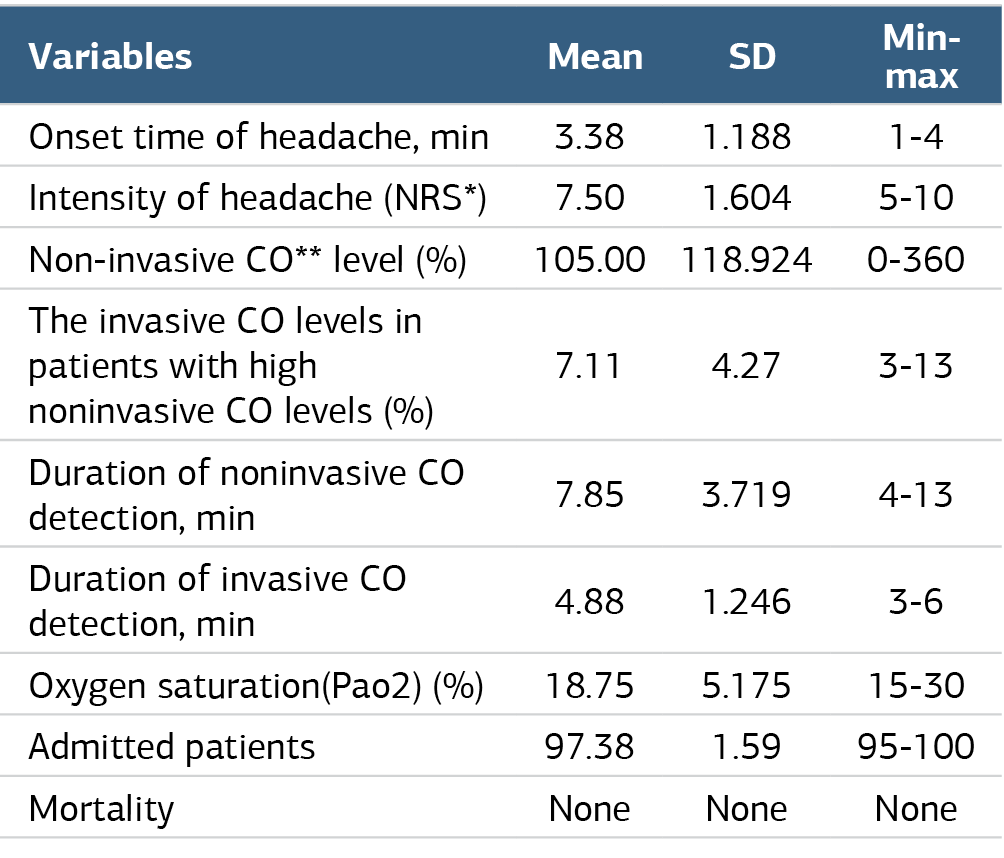
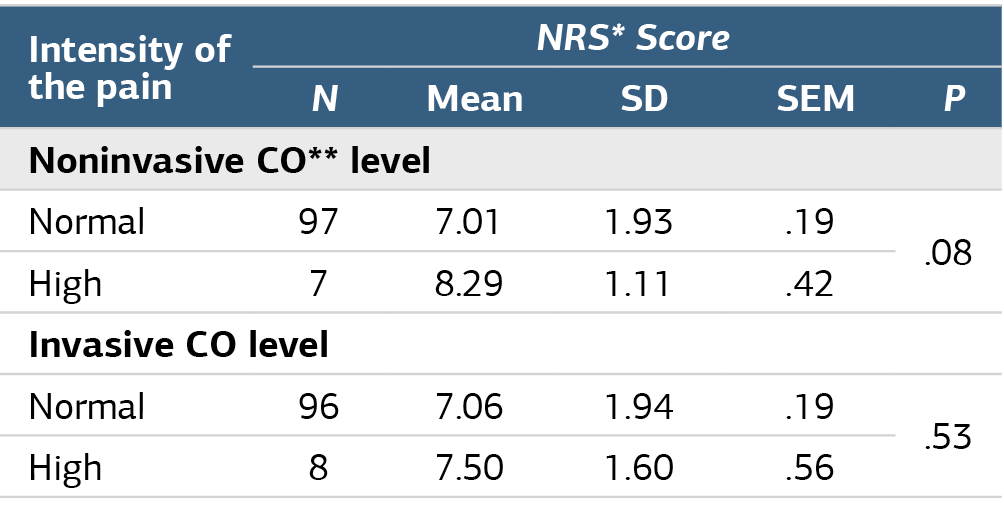
Patients with elevated CO levels detected by invasive measurement were asked to rate the severity of their pain on the Numeric Rating Scale (NRS), with scores ranging from 1 to 10. The mean NRS score of all patients was 7.05 ± 1.91, with scores ranging from 1 to 10. The NRS scores of patients with confirmed CO poisoning by invasive measurement averaged 7.50 ± 1.60, ranging from 5 to 10.
The mean SpCO level in patients with elevated CO was 7.11 ± 4.27%, ranging from 3% to 13%. In the same group, the mean COHb level was 7.85 ± 3.71%, ranging from 4% to 13%.
The time to obtain the SpCO result ranged from 3 to 6 minutes among the eight patients with elevated CO levels, with a mean of 4.88 ± 1.24 minutes. Invasive CO detection times ranged from 15 to 30 minutes, with a mean of 18.75 ± 5.17 minutes. The saturation values for these patients averaged 97.38 ± 1.59%, ranging from 95% to 100%. Of the eight patients with elevated CO levels, there were no hospital admissions or mortality (Table 2).
The NRS scores of patients were analyzed, and no significant difference was observed between patients with normal and elevated CO levels, regardless of whether the levels were measured noninvasively or invasively (Table 3).
Tobacco and tobacco product use were evaluated in patients with elevated CO levels. Among these patients, 37.5% (n = 3) reported smoking, 25% (n = 2) reported being passive smokers, and 37.5% (n = 3) stated that they did not use tobacco or tobacco products.
Discussion
Carbon monoxide (CO) poisoning is a life-threatening condition that can manifest with various symptoms. One of the early symptoms of acute intoxication is headache. However, there is no specific symptom or physical examination finding that is unique to CO poisoning. This lack of specificity can lead to diagnostic delays and may result in the condition being overlooked. Although the reported frequency of CO poisoning cases is approximately 0.0137% (around 14 per 100,000), with a mortality rate of about 0.00005% (5 per 10 million), the true incidence of CO poisoning is unknown, as many cases likely go undetected.11,12 Diagnosis relies heavily on clinical suspicion and confirmation through COHb level measurement via blood gas analysis. Early diagnosis is critical, yet the subtlety of its clinical presentation often leads to delays. Our study reinforces the utility of noninvasive CO monitoring as an adjunct to routine triage protocols, particularly in emergency department settings.
Among the 45,600 patients who presented to the emergency department with a green triage code, 104 patients with isolated headaches were included in the study. Of these, seven patients were found to have elevated CO levels using noninvasive methods, while eight were identified using invasive methods. Notably, two patients with expected noninvasive results were found to have elevated levels through invasive testing, whereas one patient with an expected invasive result showed elevated levels noninvasively. Consistent with previous studies that employed noninvasive CO screening in emergency departments, our findings underscore the importance of SpCO measurement in detecting and managing covert CO poisoning cases early. Roth et al. screened 16,108 emergency department patients using SpCO measurements over one year and identified 17 cases of CO poisoning.13 Similarly, Suner et al. reported 11 cases of covert CO poisoning among 10,856 screened patients.14 Integrating noninvasive CO monitoring into the initial triage process has the potential to transform emergency department workflows, particularly in high-volume settings. Routine SpCO screening in emergency departments has been shown to improve the detection of CO poisoning and patient outcomes by reducing the time to treatment.14 Our findings support this approach and highlight the need to train emergency personnel to use these devices.
Carbon monoxide poisoning is more commonly observed during the winter months, coinciding with increased use of heating systems and prolonged indoor exposure. Previous research has also documented a rise in CO poisoning cases during cold months such as November, December, and January.15-17 Our study, conducted during the winter months, observed a similar trend. However, regional differences in heating methods and environmental factors may influence these findings. Multicenter studies are needed to explore these variations further and provide region-specific recommendations for prevention and early detection.
In this study, we specifically focused on patients presenting with isolated headaches, the most common symptom of CO poisoning. By targeting this group, we aimed to identify cases that might otherwise go undiagnosed. Variations in the study population and timeframes can yield differing results and observations. Our study’s smaller sample size compared to other investigations may be attributed to our focus on admissions during the winter months and the selection of patients with isolated headaches.
While the most common symptoms of CO poisoning may vary across studies, headache remains consistently reported as a primary symptom. Previous research has reported headache frequencies ranging from 54% to 55% in CO poisoning cases.18-20 Moreover, headaches can occur even at COHb levels below 10%.4,21
In our study, patients presenting with isolated headaches, the most common symptom, were explicitly evaluated. Assessing patients based on the most frequent presenting symptom may enhance the detection of CO poisoning. However, in routine practice, patients with isolated headaches are often diagnosed with primary headache syndromes, leading to potential underdiagnosis of CO poisoning.
Zorbalar et al. analyzed 482 patients, of whom 186 (38.6%) were male, with a mean age of 38.0 ± 15.6 years. In this study, 23 patients (74.2%) diagnosed with CO poisoning were female, with a mean age of 33.6 ± 14.9 years.22 Another study involving 323 patients diagnosed with CO poisoning reported a mean age of 29 ± 17 years, with females comprising the majority (64%). Heckerling et al. evaluated 89 emergency department patients presenting with headache or dizziness; among them, 63 were female, and 26 were male, with a mean age of 39.2 years.4 Chan et al. found that 54% of 93 patients with acute CO poisoning were female, while 46% were male.23 Conversely, a study by Hampson et al., involving 1,473 individuals, found that males accounted for a larger proportion (65%).19 A retrospective study in Türkiye spanning 14 years indicated that females were more frequently exposed to CO poisoning than males.20 In our study, 68 (65.4%) of the 104 patients were female, while 36 (34.6%) were male, with a mean age of 37.56 ± 13.96 years. Among patients with elevated CO levels detected invasively, the mean age was 41 ± 16.31 years. Among those with elevated CO levels detected noninvasively, 57.1% were female, while this proportion rose to 75% among those measured invasively.20 This gender discrepancy is often attributed to sociocultural factors, including increased time spent indoors and proximity to household sources of CO, such as stoves and heaters. At the same time, males are more likely to be outdoors or in workplace environments. Future research should explore the intersection of gender roles, occupational exposure, and CO poisoning risks to develop targeted prevention strategies.
Limitations
Our study was conducted at a single center in a region where harsh winter conditions are uncommon. As such, our findings may not fully reflect the rates of CO poisoning in areas where cold climates and heavy reliance on stoves or other combustion-based heating systems are more common. Regions with intensive stove use are likely to experience higher incidences of CO exposure, and this limitation may have contributed to the relatively low number of CO poisoning cases identified in our study.
Additionally, the study population was limited to patients presenting with isolated headaches, which may not encompass the broader spectrum of symptoms associated with CO poisoning. By focusing solely on the winter season, we may also have excluded cases occurring at other times of the year when different sources of CO exposure might be relevant, such as motor vehicles or industrial processes.
Another limitation is the reliance on noninvasive and invasive CO measurements as diagnostic tools, which, while helpful, are not without potential errors. Variability in the accuracy of these methods, especially in patients with borderline results, underscores the need for standardized protocols and complementary diagnostic criteria.
Finally, the study’s single-center design and limited sample size reduce its generalizability. Future multicenter studies involving diverse geographic regions, larger and more heterogeneous populations, and year-round data collection are warranted to address these limitations. Such studies would help better understand the regional and seasonal variations in CO poisoning and provide a more comprehensive understanding of its epidemiology and early detection strategies.
Conclusion
Considering noninvasive CO values as an additional parameter during the initial assessment of a patient’s vital signs at admission can aid in the early detection of CO poisoning, facilitating timely diagnosis and treatment for affected individuals.
Declarations
Ethics Declarations
This study was approved by the Ethics Committee of İzmir Katip Celebi University (Date: 2020-05-12, No: IRB#: 640)
Animal and Human Rights Statement
All procedures performed in this study were in accordance with the ethical standards of the institutional and/or national research committee and with the 1964 Helsinki Declaration and its later amendments, or comparable ethical standards.
Informed Consent
Written informed consent was obtained from all participants.
Data Availability
The data supporting the findings of this study are available from the corresponding author on reasonable request.
Conflict of Interest
The authors declare no conflict of interest.
Funding
None.
Author Contributions (CRediT Taxonomy)
Conceptualization: A.A., Z.K.
Methodology: A.A., Z.K., P.Y.A.
Formal Analysis: A.A., F.E.T.
Investigation: A.A., Z.K., P.Y.A., İ.K., F.E.T.
Data Curation: A.A., Z.K.
Writing – Original Draft: A.A.
Writing – Review & Editing: Z.K., P.Y.A., İ.K., F.E.T.
Supervision: Z.K., F.E.T.
AI Usage Disclosure
The authors declare that no AI-assisted technologies were used.
Abbreviations
CO: Carbon monoxide
IRB: Institutional review board
NRS: Numeric rating scale
SPSS: Statistical package for the social sciences
References
- Otterbein LE, Foresti R, Motterlini R. Heme oxygenase-1 and carbon monoxide in the heart: the balancing act between danger signaling and pro-survival. Antioxidants (Basel). 2022;11(1):109.
- Rose JJ, Wang L, Xu Q, et al. Carbon monoxide poisoning: pathogenesis, management, and future directions of therapy. Am J Respir Crit Care Med. 2017;195(5):596-606. doi:10.1164/rccm.201606-1275ci
- Andresen JJ, Shafi NI, Durante W, Bryan RM Jr. Effects of carbon monoxide and heme oxygenase inhibitors in cerebral vessels of rats and mice. Am J Physiol Heart Circ Physiol. 2006;291(1):H223-30. doi:10.1152/ajpheart.00058.2006
- Wang XP, Zheng WC, Bai Y, et al. Carbon monoxide-releasing molecule-3 alleviates Kupffer cell pyroptosis induced by hemorrhagic shock and resuscitation via sGC-cGMP signal pathway. Inflammation. 2021;44(4):1330-44. doi:10.1007/s10753-021-01419-w
- Badaeva A, Maiolino L, Danilov A, Naprienko M, Danilov A, Jacob UM, Calabrese V. Neurogasobiology of migraine: Carbon monoxide, hydrogen sulfide, and nitric oxide as emerging pathophysiological trinacrium relevant to nociception regulation. Open Med (Wars). 2025;20(1):20251201. doi:10.1515/med-2025-1201
- Mardimae A, Balaban DY, Machina MA, et al. The interaction of carbon dioxide and hypoxia in the control of cerebral blood flow. Pflugers Arch. 2012;464(4):345- 51. doi:10.1007/s00424-012-1148-1
- Bilska-Wilkosz A, Górny M, Iciek M. Biological and Pharmacological Properties of Carbon Monoxide: A General Overview. Oxygen. 2022;2(2):130-151. doi:10.3390/oxygen2020012
- Harrigan MF. Headache. In: Tintinalli J, editor. Tintinalli’s emergency medicine: a comprehensive study guide. 8th ed. New York, NY: McGraw-Hill Education; 2016:1131-7.
- Kowalski RG, Claassen J, Kreiter KT, et al. Initial misdiagnosis and outcome after subarachnoid hemorrhage. JAMA. 2004;291(7):866-9. doi:10.1001/jama.291.7.866
- Ernst A, Zibrak JD. Carbon monoxide poisoning. N Engl J Med. 1998;339(22):1603-8. doi:10.1056/nejm199811263392206
- Satran D, Henry CR, Adkinson C, Nicholson CI, Bracha Y, Henry TD. Cardiovascular manifestations of moderate to severe carbon monoxide poisoning. J Am Coll Cardiol. 2005;45(9):1513-6. doi:10.1016/j.jacc.2005.01.044
- Prockop LD, Chichkova RI. Carbon monoxide intoxication: an updated review. J Neurol Sci. 2007;262(1-2):122-30. doi:10.1016/j.jns.2007.06.037
- Roth D, Herkner H, Schreiber W, et al. Accuracy of noninvasive multiwave pulse oximetry compared with carboxyhemoglobin from blood gas analysis in unselected emergency department patients. Ann Emerg Med. 2011;58(1):74-9. doi:10.1016/j.annemergmed.2010.12.024
- Suner S, Partridge R, Sucov A, et al. Noninvasive pulse CO-oximetry screening in the emergency department identifies occult carbon monoxide toxicity. J Emerg Med. 2008;34(4):441-50. doi:10.1016/j.jemermed.2007.12.004
- Shotar AM, Shatnawi R, Halalsheh M, et al. Epidemiological study of carbon monoxide deaths in North Jordan, 2009-2018. Mater Sociomed. 2021;33(3):184- 7. doi:10.5455/msm.2021.33.184-187
- Partrick M, Fiesseler F, Shih R, Riggs R, Hung O. Monthly variations in the diagnosis of carbon monoxide exposures in the emergency department. Undersea Hyperb Med. 2009;36(3):161-7.
- Metin S, Yıldız Ş, Çakmak T, Demirbaş Ş. 2010 yılında Türkiye’de karbonmonoksit zehirlenmesinin sıklığı [Frequency of carbon monoxide poisoning in Türkiye in 2010]. TAF Prev Med Bull. 2011;10(5):587-92. doi:10.5455/pmb.20110417125648
- Keles A, Demircan A, Kurtoglu G. Carbon monoxide poisoning: how many patients do we miss? Eur J Emerg Med. 2008;15(3):154-7.
- Hampson NB, Dunn SL, UHMCS/CDC CO Poisoning Surveillance Group. Symptoms of carbon monoxide poisoning do not correlate with the initial carboxyhemoglobin level. Undersea Hyperb Med. 2012;39(2):657-65.
- Arıcı AA, Demir Ö, Özdemir D, Ünverir P, Tunçok Y. Acil servise başvuran karbonmonoksit maruz kalımları: on dört yıllık analiz [Carbon monoxied exposures admitted to emergency department: fourteen years analysis]. DEU Tıp Derg. 2010;24(1):25-32.
- Arngrim N, Schytz HW, Hauge MK, Ashina M, Olesen J. Carbon monoxide may be an important molecule in migraine and other headaches. Cephalalgia. 2014;34(14):1169-80. doi:10.1177/0333102414534085
- Zorbalar N, Yesilaras M, Aksay E. Carbon monoxide poisoning in patients presenting to the emergency department with a headache in winter months. Emerg Med J. 2014;31(e1):e66-70. doi:10.1136/emermed-2012-201712
- Chan MY, Au TTs, Leung KS, Yan WW. Acute carbon monoxide poisoning in a regional hospital in Hong Kong: historical cohort study. Hong Kong Med J. 2016;22(1):46-55. doi:10.12809/hkmj144529
Tables
Table 1. Clinical and diagnostic characteristics of included patients
Numeric Rating Scale **Carbon Monoxide
Table 2. Analysis of patients with elevated carbon monoxide levels
* Numeric Rating Scale **Carbon Monoxide
Table 3. Comparison of pain intensities between patients with elevated and normal carbon monoxide levels
* Numeric Rating Scale **Carbon Monoxide
Additional Information
Publisher’s Note
Bayrakol MP remains neutral with regard to jurisdictional and institutional claims.
Rights and Permissions

This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License (CC BY-NC 4.0). To view a copy of the license, visit https://creativecommons.org/licenses/by-nc/4.0/
About This Article
How to Cite This Article
Ahmet Altaş, Zeynep Karakaya, Pınar Yeşim Akyol, İbrahim Korkmaz, Fatih Esad Topal. The value of noninvasive carbon monoxide measurement in the early diagnosis of patients with headache during winter months. Ann Clin Anal Med 2026;17(9):911-915. doi:10.4328/ACAM.22636
Publication History
- Received:
- 06.03.2025
- Accepted:
- 23.06.2025
- Published Online:
- 10.07.2025
- Printed:
- 01.09.2026