
Abstract
IntroductionOsteochondromas are benign bone tumors with a cap of hyaline cartilage. Case PresentationAn 80-year-old female patient visited the neurology clinic with a complaint of headache. A calcified, pedunculated mass was detected in the left middle cranial fossa on non-contrast computed tomography images. ConclusionOsteochondromas should also be considered in the differential diagnosis of intracranial bone lesions.
Keywords
Introduction
Osteochondromas are benign tumors composed of cortical and medullary bone with an overlying hyaline cartilage cap. Furthermore, they must demonstrate continuity with the underlying parent bone cortex and medulla. They are developmental lesions rather than true neoplasms. The radiologic features of osteochondromas are often pathognomonic and reflect their pathological appearance.1-2 Intracranial osteochondromas are relatively rare, representing 0.1-0.2% of all intracranial tumors.1,3 The literature consists only of sporadic case reports. We present an uncommon case of osteochondroma in the middle cranial fossa, originating from the sphenoid bone
Case Presentation
An 80-years old woman visited the neurology clinic complaining of a headache that lasted for 1 month. Neurological examination was unremarkable. On non-contrast computed tomography images, a calcified pedunculated solid mass measuring 18 × 13 × 16 mm located in the left middle cranial fossa was detected (Figure 1). The mass appeared to be continuous with medulla of the underlying bone through a hypodense gap, compatible with cartilage tissue. No change in the characteristics or size of the mass was observed in follow-up CT images. On the non-contrast MRI images, an extra axial mass hyperintense in T1WI and T2WI, and hypointense in SWI was observed, with peripheral hypointense thin (<1 mm) cartilage cap (Figure 2). No peripheral edema was seen. Nearby cerebral parenchyma was minimally displaced. In this case, the mass was considered to be benign and unrelated to the patient’s current complaints. Due to advanced age, chronic conditions and the relative absence of mass effect, the patient was not considered a candidate for surgery. Consequently, pathological confirmation of the diagnosis was not made.Ethical ApprovalNot applicable.Statistical AnalysisNot applicable.
This case report was prepared in accordance with the CARE guidelines.
Discussion
Although osteochondromas tend to be benign, there is a slight possibility of around 1% for malignant transformation.2 The thickness of the cartilage cap seen in MRI helps to assess the possibility of malignant transformation. Cartilage cap thickness of more than 2 cm indicates the possible malignant change.3-5
Intracranial osteochondromas may arise at any age with the peak incidence in the third decade.6 Because of the rare incidence of intracranial osteochondromas, the differential diagnosis with other more commonly found tumors, such as meningioma becomes essential. Differential diagnosis based on radiological findings also include osteosarcoma and other miscellaneous osteomatous lesions. Non-contrast CT scans usually show from hyperdense to isodense mass for meningiomas, and calcification is commonly seen.7
Meningiomas are extra axial tumors and most common tumor of the meninges. They are typically well-rounded lesions originating from dura mater and characteristically exhibit ‘dural tail’ sign.7 In this case mass lesion’s origin from bony tissue excludes meningiomas. The mass’ non-progressive nature during the follow-up scans, presence of cartilage cap and typical continuous appearance with the underlying bone medulla suggests osteochondroma to be the most likely diagnosis. Clinical manifestation of intracranial osteochondromas mostly depends on the tumor mass effect and location.8
Limitations
The main limitation of this case is the lack of histopathological confirmation, as surgical intervention was not performed. The diagnosis was therefore based on characteristic radiological findings and follow-up imaging.
Conclusion
In light of the literature and imaging findings, osteochondromas should be included in the differential diagnosis list of intracranial bone lesions.
Declarations
Animal and Human Rights Statement
All procedures performed in this study were in accordance with the ethical standards of the institutional and/or national research committee and with the 1964 Helsinki Declaration and its later amendments or comparable ethical standards.
Informed Consent
Written informed consent was obtained from the patient.
Data Availability
The datasets used and/or analyzed during the current study are not publicly available due to patient privacy reasons but are available from the corresponding author on reasonable request.
Conflict of Interest
The authors declare that there is no conflict of interest.
Funding
None.
Abbreviations
CT: Computed tomography
MRI: Magnetic resonance imaging
SWI: Susceptibility-weighted imaging
T1WI: T1-weighted imaging
T2WI: T2-weighted imaging
References
- Pontes Í, Leão R, Lobo C, Paula V, Yamachira V, Baptista A, et al. Imaging of solitary and multiple osteochondromas: from head to toe—a review. Clin Imaging. 2023;103(1):1-3. doi:10.1016/j.clinimag.2023.109989
- Murphey MD, Choi JJ, Kransdorf MJ, Flemming DJ, Gannon FH. Imaging of osteochondroma: variants and complications with radiologic-pathologic correlation. Radiographics. 2000;20(5):1407-1427. doi:10.1148/radiographics.20.5.g00se171407
- Venkata RI, Kakarala SV, Garikaparthi S, Duttaluru SS, Parvatala A, Chinnam A. Giant intracranial osteochondroma: a case report and review of the literature. Surg Neurol Int. 2011;2(1):118-122. doi:10.4103/2152-7806.84242
- Hongo H, Oya S, Abe A, Matsui T. Solitary osteochondroma of the skull base: a case report and literature review. J Neurol Surg Rep. 2015;76(1):13-17. doi:10.1055/s-0034-1387189
- Padhya TA, Athavale SM, Kathju S, Sarkar S, Mehta AR. Osteochondroma of the skull base. Otolaryngol Head Neck Surg. 2007;137(1):166-168. doi:10.1016/j.otohns.2007.01.005
- Erdogan S, Zorludemir S, Erman T, Akgul E, Ergin M, Ildan F, et al. Chondromas of the falx cerebri and dural convexity: report of 2 cases and review of the literature. J Neurooncol. 2006;80(1):21-24. doi:10.1007/s11060-005-9082-0
- Buerki RA, Horbinski CM, Kruser T, Horowitz PM, James CD, Lukas RV. An overview of meningiomas. Future Oncol. 2018;14(21):2161-2177. doi:10.2217/fon-2018-0006
- Omalu B, Wiley C, Hamilton R. February 2003: a 53-year-old male with new onset seizures. Brain Pathol. 2003;13(3):419-421. doi:10.1111/j.1750-3639.2003.tb00046.x
Figures
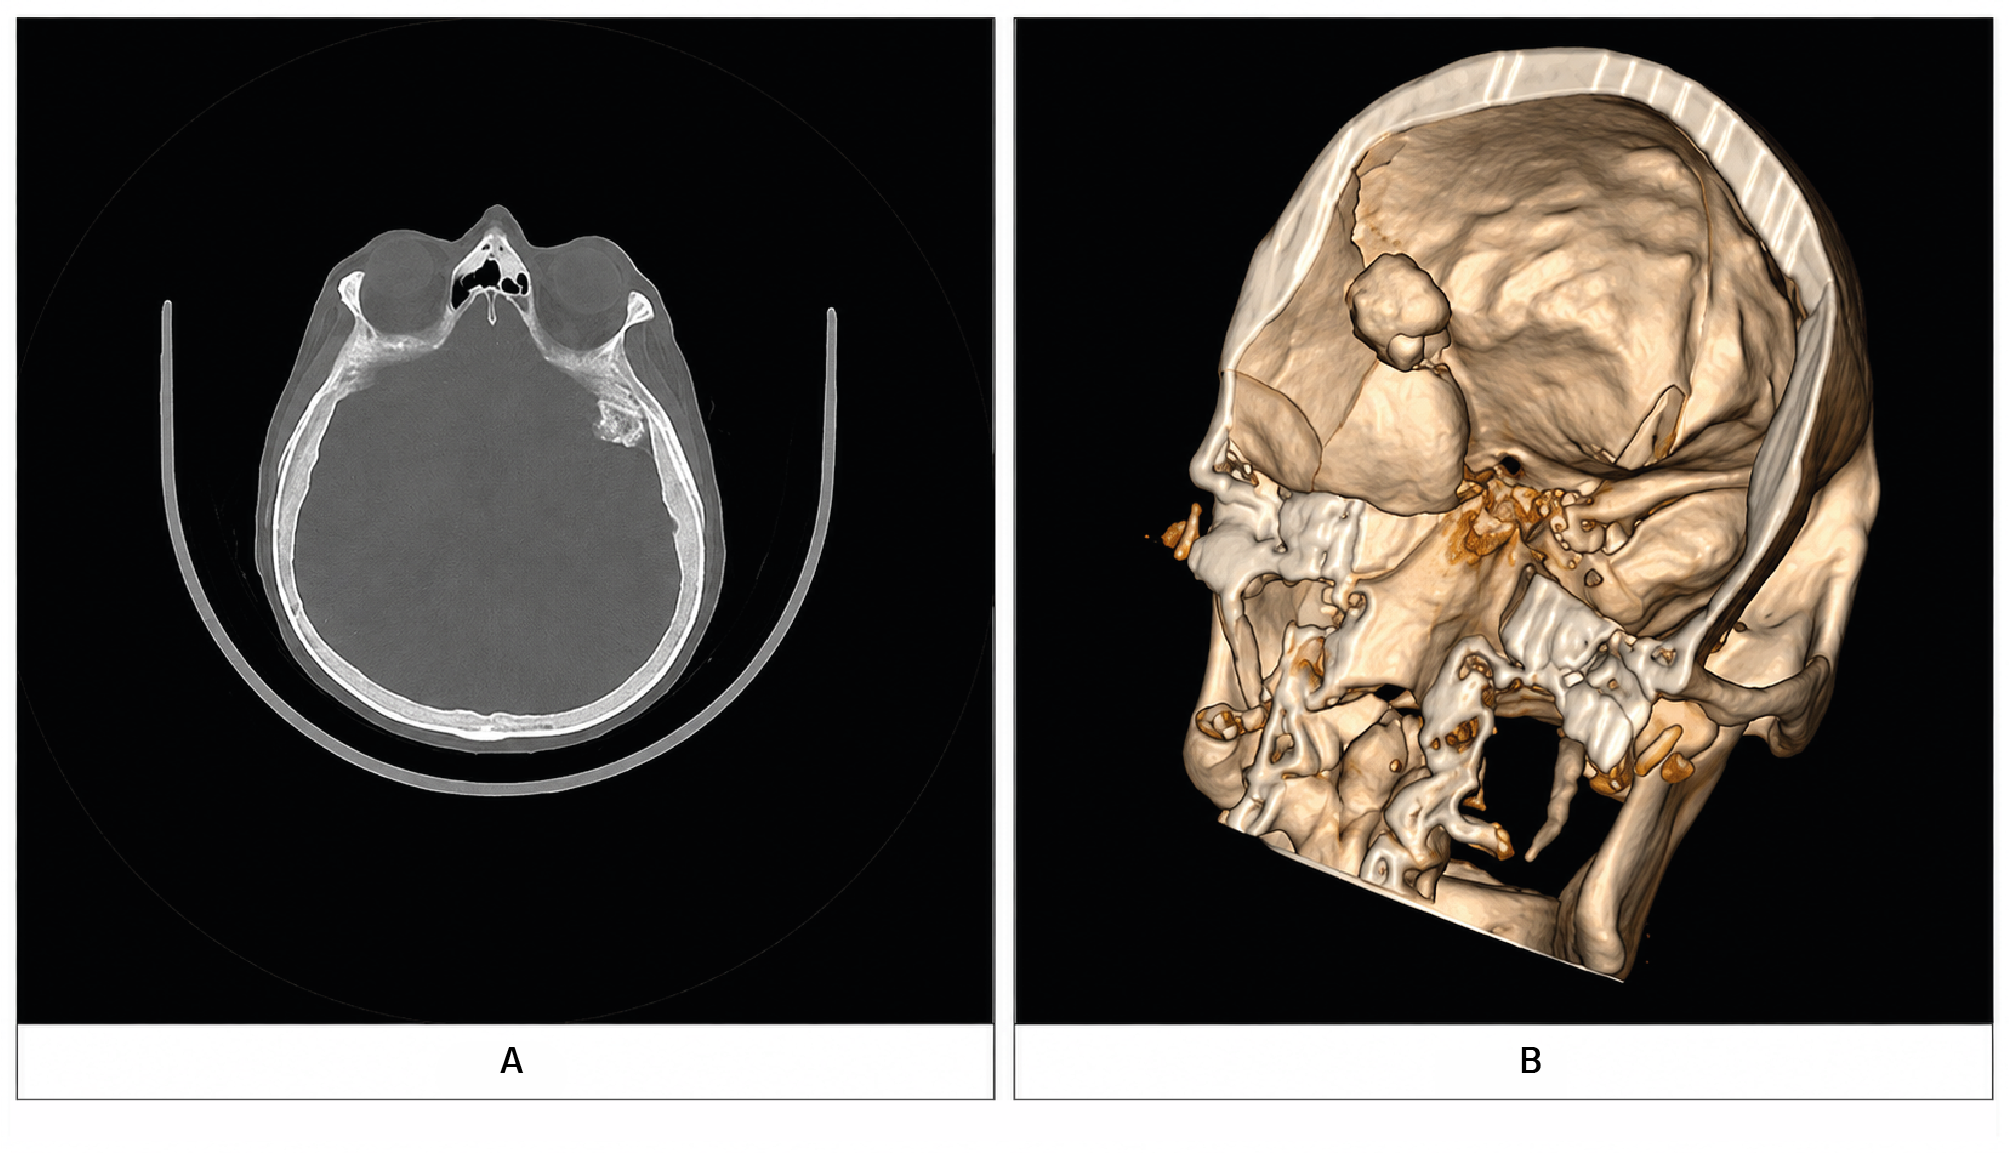
Figure 1. Computed Tomography Findings
(A) Noncontrast computed tomography image in the axial plane shows a pedunculated solid bony mass located in the left middle cranial fossa. (B) Threedimensional reconstructed image demonstrates that the mass originates from the left greater wing of the sphenoid bone.
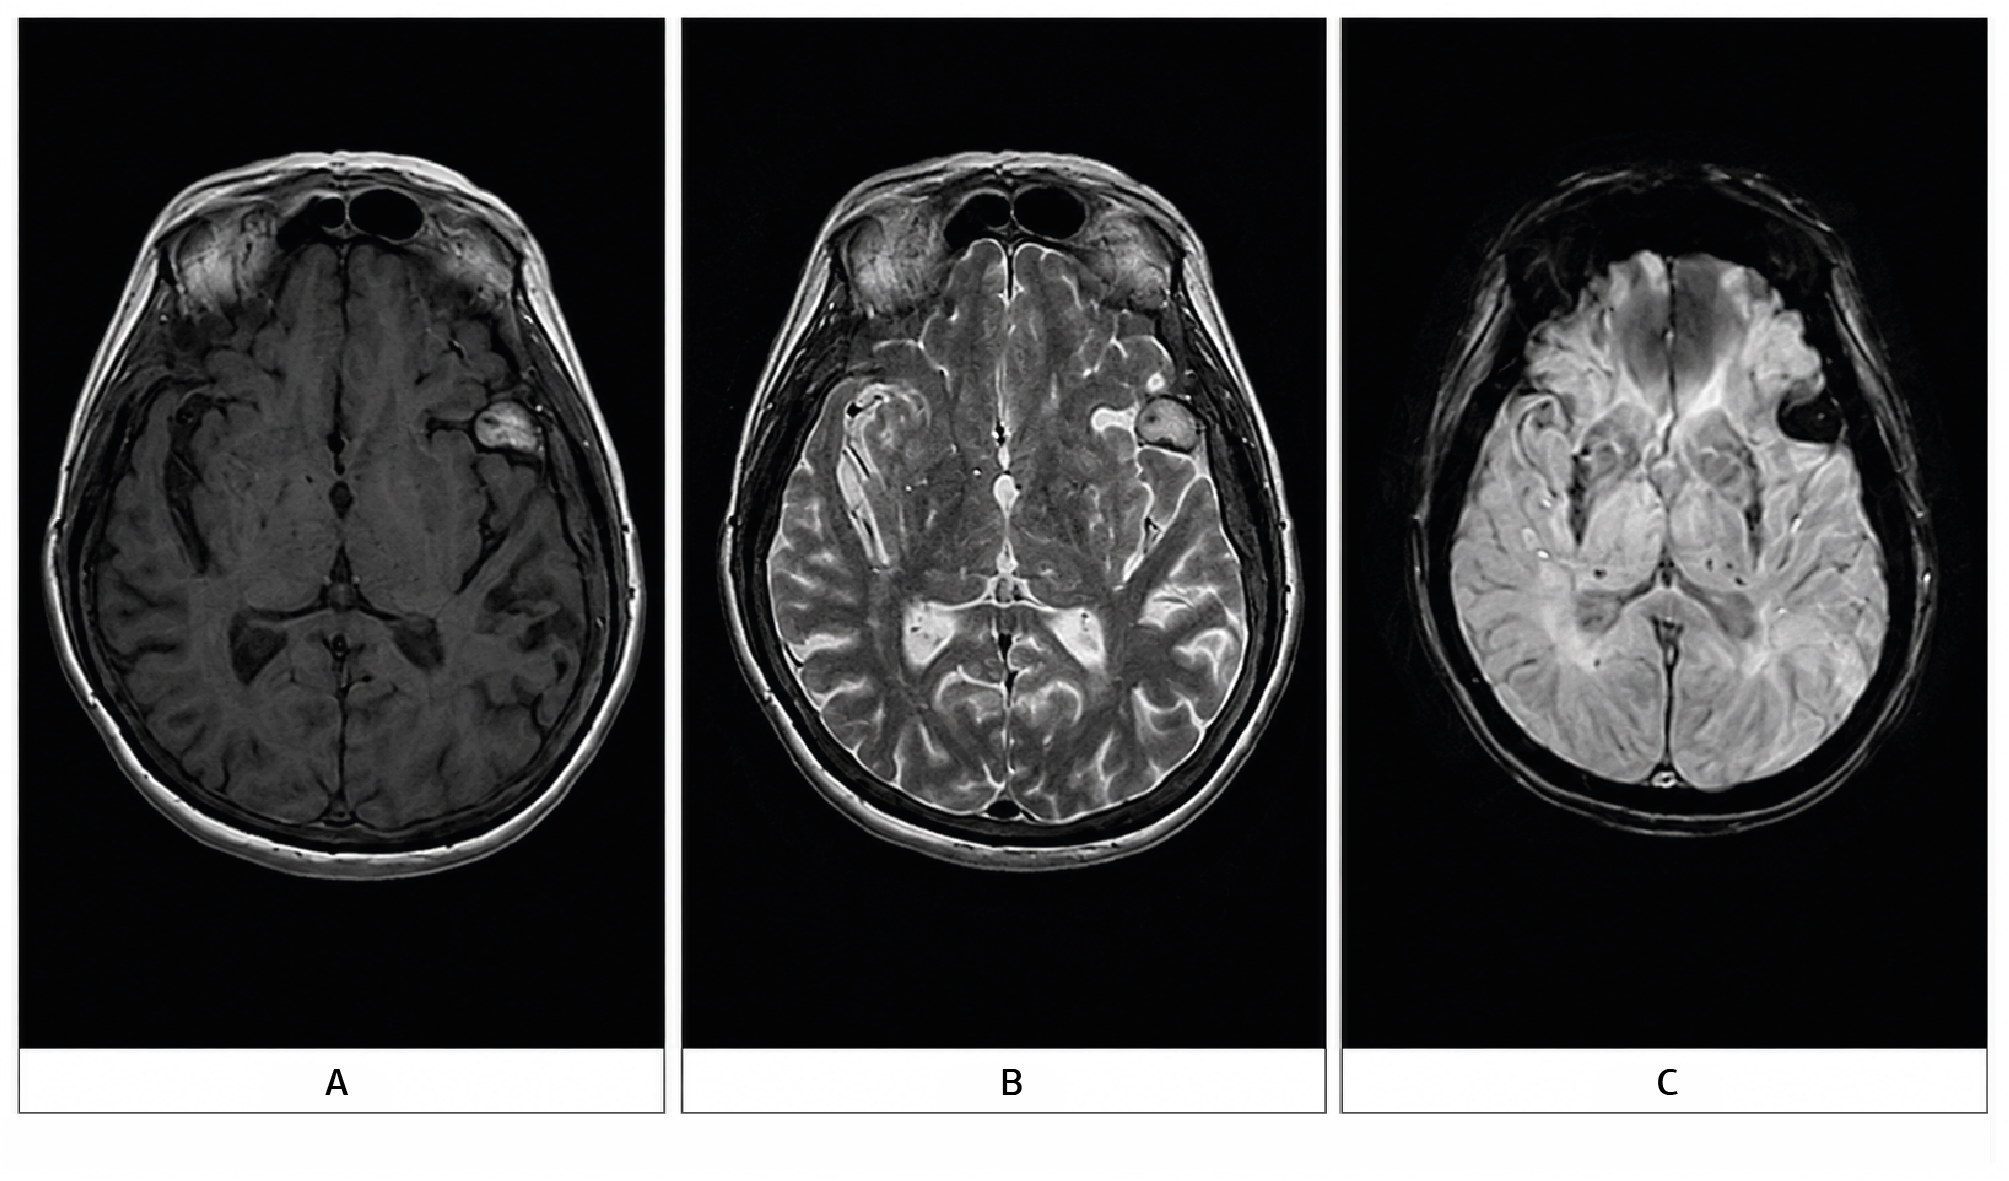
Figure 2. Magnetic Resonance Imaging Findings
T1-weighted (A), T2-weighted (B), and susceptibility-weighted (C) images reveal an extra-axially located mass with high signal intensity on T1-weighted and T2-weighted images and low signal intensity on susceptibility-weighted imaging.
Additional Information
Publisher’s Note
Bayrakol MP remains neutral with regard to jurisdictional and institutional claims.
Rights and Permissions

This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License (CC BY-NC 4.0). To view a copy of the license, visit https://creativecommons.org/licenses/by-nc/4.0/
About This Article
How to Cite This Article
Hakan Şahinoğlu, Sırrı Gürhan Çelen, Murat Baykara. Osteochondroma: in a rare location inside of the skull: A Case Report. Ann Clin Anal Med 2024;15(Suppl 2):70-72. doi:10.4328/ACAM.22046
Publication History
- Received:
- 13.11.2023
- Accepted:
- 22.01.2024
- Published Online:
- 29.03.2024
- Printed:
- 20.10.2024